BIGGER PICTURE Better care
The hospital records that can raise a sepsis alarm
Hospital records contain many clues, spread across time and screens. TREWS tried to turn those clues into a timely clinical review before a dangerous infection response was missed.
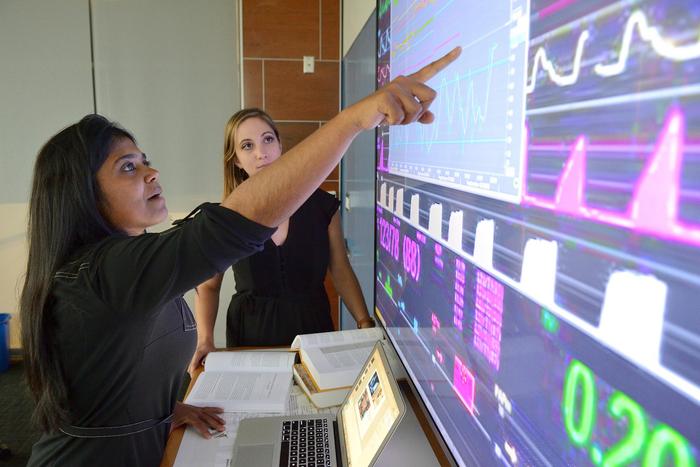 Original photograph
- Study hospitals
- Five
- Flagged sepsis cases analysed
- 6,877
- Adjusted mortality difference
- 3.3 percentage points
How the idea works
Combine clinical clues
Records supply evolving measurements and context.
Request a sepsis review
The model flags a concerning pattern.
Confirm and treat
Clinicians assess the patient and choose appropriate action.
The signs do not arrive as one tidy diagnosis
Sepsis can begin with findings that also occur in other conditions. TREWS combines information from the electronic health record to identify a pattern that merits attention. Its purpose is to get a clinician to assess the patient sooner, not to let a risk score independently decide that an infection exists.
Sources: [2]
A warning inside the clinical workflow
The alert appears where care teams already work with patient information. Clinicians can review and confirm the concern, then make treatment decisions. This differs from an algorithm tested silently in the background: the intervention includes how people encounter, interpret and respond to its prediction. A good prediction cannot help a patient if nobody responds.
The patients behind the mortality result
The 2022 analysis examined 6,877 sepsis patients flagged before antibiotics. When clinicians confirmed the alert within three hours, adjusted in-hospital mortality was 3.3 percentage points lower than in the comparison group. The often-cited relative reduction was 18.7%. The first expresses the absolute difference; the second expresses the change relative to the comparison risk.
Sources: [1]
Why response capacity belongs in the design
Patients were not randomly assigned to prompt or delayed confirmation. Differences in teams, patients and attention could contribute despite statistical adjustment. TREWS illustrates actionable prediction with encouraging clinical observations; it does not establish that installing an alert alone causes the reported mortality reduction. Response capacity belongs in the design from the beginning.
Sources: [1]
The original sources
- Nature MedicineProspective, multi-site study of patient outcomes after implementation of TREWS
- Johns Hopkins Malone CenterSepsis detection platform prevents thousands of deaths